
Semen analysis: how to read the result and what to do next
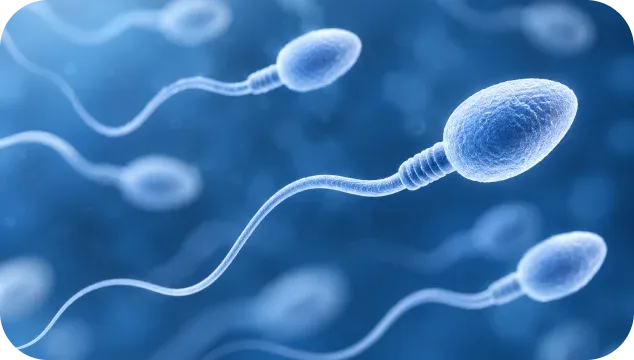
A semen analysis is the most informative and at the same time the cheapest test in a couple’s work-up. One test answers a question that otherwise takes years: is there a male factor, and how pronounced is it.
The trouble is that the result sheet looks like a table of a dozen numbers and Latin terms, and a man usually leaves the laboratory feeling he has been handed a verdict. In reality most deviations in a semen analysis are not final — and almost none of them can be read from a single number.
When to have a semen analysis
- there has been no pregnancy after 12 months of regular intercourse without contraception (or 6 months if the partner is over 35)
- before an IVF, ICSI or insemination programme
- at the pregnancy planning stage, especially after 35
- after infections, injuries or operations on the scrotum, or with a varicocele
- when planning sperm cryopreservation — for example, before treatment for cancer
- to monitor the result of treatment or surgical correction.
How to prepare: 6 rules
Poor preparation is the most common cause of “frightening” results that are not confirmed later.
- Abstinence for 2–7 days. No less and no more. One day gives a reduced volume and concentration; two weeks gives many immotile and aged sperm.
- No alcohol for 3–5 days before the test.
- No sauna, steam bath or hot bath for 7–10 days. Overheating the scrotum directly suppresses spermatogenesis.
- Do not test during an acute illness. A temperature above 38 °C spoils the results for the next 2–3 months — that is how long the sperm maturation cycle takes. After flu or Covid it makes sense to wait.
- Tell us about your medication. Antibiotics, hormonal preparations, some blood-pressure drugs and, separately, anabolic steroids have a substantial effect on the result.
- Provide the sample at the clinic. The material must reach the laboratory within an hour and must not get cold. Collecting at home and travelling by transport is a typical cause of falsely poor motility.
What each value means
Below are the reference values from the 6th edition of the WHO laboratory manual (2021) — the one modern laboratory practice follows. It is important to understand their nature: they are not a “norm of health”, but the 5th centile of values in men whose partners conceived within a year. A value slightly below the limit does not mean infertility, and a value within the range does not guarantee a pregnancy.
Note: if your result was issued under the older 5th WHO edition (2010), the limits there are different — volume 1.5 ml, concentration 15 million/ml, total motility 40%, progressive 32%, vitality 58%. The figures from the two editions should not be compared directly.
Ejaculate volume — from 1.4 ml
A smaller volume may point to an incomplete collection, a short abstinence, an obstruction or retrograde ejaculation. On its own, volume is the least important value.
Concentration — from 16 million/ml, total count — from 39 million
These are the basic figures. A reduced concentration is called oligozoospermia, a complete absence of sperm azoospermia, and an extremely small number found only after centrifugation cryptozoospermia.
Motility: total — from 42%, progressive — from 30%
The most important value, together with concentration. What matters is progressive motility — sperm that move forward rather than on the spot. Reduced motility is asthenozoospermia.
Morphology — from 4% normal forms
The figure “4%” shocks patients most: it seems that 96% of the sperm are defective. That is true — and it is the physiological norm for humans. Assessment by the strict Kruger criteria is deliberately harsh. A reduced share of normal forms is teratozoospermia.
Vitality — from 54%
Shows the share of live sperm. It is especially important when motility is low: it distinguishes “the sperm are dead” from “alive but immotile” — different causes and different tactics.
pH — from 7.2, leukocytes — under 1 million/ml
Unlike the previous ones, these two values are not centile limits but agreed thresholds. Raised leukocytes (leukocytospermia) point to an inflammatory process that needs separate investigation.
Liquefaction time, aggregation, agglutination
Agglutination — sperm sticking to one another — may indicate an immunological factor. In that case a MAR test for antisperm antibodies is ordered.
One semen analysis proves nothing
This is the main thing to remember. The same man’s semen values fluctuate widely depending on abstinence, stress, a recent illness, the season and even the quality of sleep.
So when there are deviations, the test is repeated after 2–4 weeks, in the same laboratory and with the same preparation. A diagnosis is made on two or three tests, not on one sheet.
There are known cases where a “catastrophic” first analysis turned out perfectly workable after proper preparation and a repeat — and the reverse, where a problem was missed on the strength of one good result.
Additional tests
When a basic semen analysis is not enough:
- MAR test — antisperm antibodies, the immunological factor in infertility
- sperm DNA fragmentation test — a separate measure of the quality of the genetic material. A normal semen analysis with high DNA fragmentation happens, and that is sometimes what explains recurrent pregnancy loss or IVF failures with “good” tests
- semen biochemistry (fructose, zinc, α-glucosidase) — helps to localise the problem
- bacterial culture and PCR for infections in leukocytospermia
- hormone profile: FSH, LH, total testosterone, prolactin, oestradiol, sometimes inhibin B
- karyotyping and analysis of the Y-chromosome AZF locus — mandatory in azoospermia and severe oligozoospermia
- scrotal ultrasound with Doppler — to detect a varicocele, cysts or signs of obstruction.
What to do with a poor result
Step 1. Find the cause
The most common causes that can genuinely be corrected:
- varicocele — dilated veins of the scrotum; operated on where indicated, after which the values often improve
- infections and inflammatory processes — treated
- hormonal disorders — corrected with medication
- obstruction of the vas deferens — resolved surgically or bypassed by retrieving sperm directly from testicular tissue
- lifestyle and external factors — nicotine, excess weight, overheating, anabolic steroids, some medication, occupational hazards.
Primary testicular damage — after orchitis, chemotherapy or injury, or with genetic conditions — is often irreversible, but even then options remain.
Step 2. Give the body 3 months
Since a full cycle of spermatogenesis takes about 72–74 days, any treatment or lifestyle change is assessed no earlier than 3 months later. A follow-up analysis before then simply will not show the effect.
What works over those three months: giving up nicotine, normalising weight, avoiding saunas and hot baths, moderate physical activity, proper sleep, treating any infections found, and antioxidant therapy as prescribed by a doctor.
Step 3. Choose the way to achieve a pregnancy
Even with pronounced deviations there are solutions today:
- ICSI — the embryologist injects a single selected sperm cell straight into the egg. Literally a handful of live sperm is enough for fertilisation
- PICSI — additional selection of mature sperm
- TESA, PESA, TESE, MESA — retrieving sperm directly from the testis or epididymis in azoospermia. A real route to becoming a biological father even when there is not a single sperm cell in the ejaculate
- donor sperm — the option when a man’s own sperm cannot be obtained.
All these methods are available in the infertility treatment programmes of the Ekstramed clinic in Ivano-Frankivsk.
Frequently asked questions
Is the procedure painful? No. A semen analysis is a non-invasive test; the sample is obtained by masturbation in a private room at the clinic.
How long does the result take? Usually 1–2 working days. Kruger morphology and additional tests may take longer.
What if the analysis says “azoospermia”? Don’t panic, and don’t draw conclusions from one test. The analysis should be repeated with examination of the pellet after centrifugation, hormones checked (FSH first of all), a scrotal ultrasound and a genetic work-up done. Azoospermia can be obstructive — sperm are produced but cannot get out — and that is a solvable situation.
Do supplements and vitamins help? Antioxidants can improve the values moderately, but they do not replace treating the cause. A doctor should prescribe them, not an advert.
Does a normal semen analysis mean the man is fine? Not always. There are situations with normal basic values and high DNA fragmentation or an immunological factor. So with unexplained infertility the man’s work-up does not end with a semen analysis.
Where to have a semen analysis in Ivano-Frankivsk? At the Ekstramed clinic — the test is done in our own laboratory, and the result can be discussed straight away with an andrologist. To book: the contacts section.
This article is for information only and does not replace a consultation with a doctor. Semen analysis results should be interpreted, and treatment prescribed, by an andrologist or urologist.
More worth reading
More explanations, advice and answers from the doctors of the clinic.
 01/09/2026Technology7 min readAMH and ovarian reserve: which tests really show your chances of pregnancy
 01/09/2026Technology7 min readEgg donation: when it is needed, how a donor is chosen and what the chances are
 01/09/2026Technology7 min readPrenatal screening and NIPT: a week-by-week calendar of tests in pregnancy
 01/09/2026Technology9 min readHow IVF works: every stage of the programme, step by step
- Technology01/09/20267 min readAMH and ovarian reserve: which tests really show your chances of pregnancy
- Technology01/09/20267 min readEgg donation: when it is needed, how a donor is chosen and what the chances are
- Technology01/09/20267 min readPrenatal screening and NIPT: a week-by-week calendar of tests in pregnancy
- Technology01/09/20269 min readHow IVF works: every stage of the programme, step by step